
Michael Greger's Blog
November 19, 2026
How a Plant-Based Diet Could Help Close Racial Health Gaps
Why are Black Americans sicker and die younger than their white counterparts, and what can we do about it?
During the COVID-19 pandemic, the death rate for African Americans was as much as six times higher than that of white Americans. The higher Black pandemic deaths placed a harsh spotlight on their longstanding higher mortality and diminished longevity in general. “Unfortunately, diminished [African American] life expectancy predates the COVID-19 pandemic for decades.” The Black-white death gap for women is about three years, and for men, closer to five years.
The COVID-19 death disparities may have to do with “limited access to healthy food” in predominantly Black communities, “housing density, the need to work or else, the inability to practice social distancing,” but also the underlying “burden of ill health.” Increased COVID-19 mortality and complications occur more often in people with pre-existing conditions like hypertension, obesity, diabetes, and cardiovascular disease, comorbidities that are more common among African Americans. As you can see below and at 1:25 in my video How a Plant-Based Diet Can Help Reduce Racial Health Disparities, that means more high blood pressure, more diabetes, more strokes, and more likely to die at early ages from all causes put together.
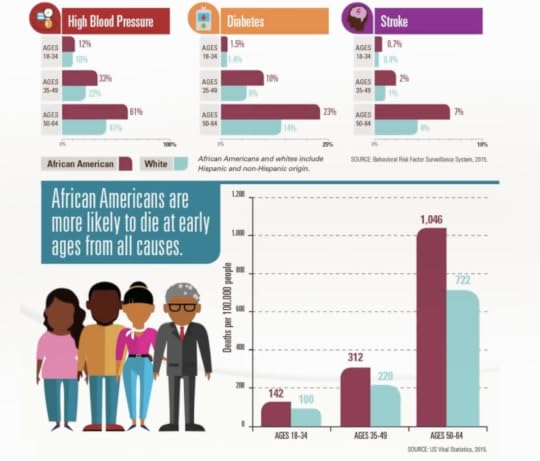
The question is why? Why do “Black Americans live sicker and die younger than their white counterparts”?
One big factor is socioeconomic status. In the United States, race is closely tied to class, with African Americans about twice as likely to be living in poverty. On average, education levels are lower as well. However, even among African Americans whose socioeconomic status is comparable to that of white people, despite higher education and more socioeconomic resources, health outcomes are still poorer. Part of that has to do with lifestyle behaviors. For example, fewer than 5% of African American adults met physical activity guidelines. Smoking rates are comparable, though African Americans tend to be exposed to more second-hand smoke and have lower quit rates. This may be because they’re more likely to use menthol cigarettes, which enhance nicotine’s addictive potential. Why menthols? Because tobacco companies’ marketing for mentholated products targets African Americans, as you can see in the ads below and at 2:43 in my video.

Black lives…Black lung.
Similarly, food messages on African American television shows reveal that not only does Black prime time contain more food commercials, but African American audiences may be receiving nearly three times as many ads for low-nutrient junk like candy and soda. That may be one reason why African Americans tend to consume fewer fruits and vegetables and are more likely to eat junkier foods. Of course, where are you going to get those fresh fruits and vegetables? There are fewer supermarkets in Black neighborhoods compared to white neighborhoods—as in, they have four times fewer supermarkets. What Black neighborhoods do excel in, though, is fast food. Predominantly Black neighborhoods have 60% more fast-food restaurants per square mile compared to predominantly white neighborhoods.
Now, of course, “dietary behaviors alone do not fully explain the significant differences in diet-related disease patterns between racial groups.” There are differences in employment, poverty, home ownership, and healthcare access, as you can see below and at 3:54 in my video.
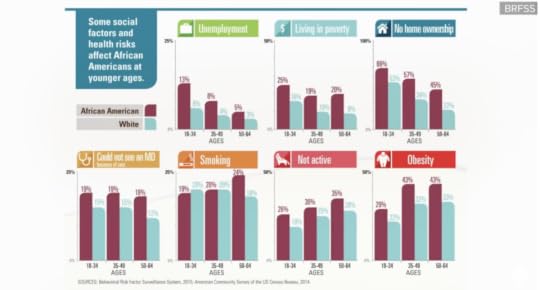
All of these factors can affect outcomes. But “[w]hile there are many social and economic factors such as racism and income inequality that contribute to health disparities, there is good evidence that simply eating a more plant-based diet could eliminate disparities in [cardiovascular disease] and diabetes.”
Here are the diabetes data. Even after controlling for education, income, physical activity, and Body Mass Index (BMI), non-Blacks eating strictly plant-based diets had 57% lower odds of diabetes. Among Black vegans, it was even more striking—70% lower odds. And that was after taking BMI into account. So, even at the same weight, Black vegans had 70% lower odds of diabetes than Black omnivores. The racial disparity is only about half that, at 36%. So, the increased risk of diabetes among Black participants was on the order of one-third, while the protection given by vegan diets in this subgroup was about 70%. Even just a vegetarian diet that includes dairy and eggs may more than counteract the racial disparity in diabetes risk.
And they are not the same weight. African Americans have higher obesity rates, cutting their lifespans by six years, but Black vegetarians and vegans have less than half the risk of obesity compared to those who eat meat. And this is after adjusting for differences in physical activity. So, even at the same exercise levels, those eating more plant-based had but a fraction of the obesity risk.
Then there is high blood pressure. In African Americans, hypertension is the most significant contributor to their increased cardiovascular disease burden and mortality. But Black vegetarians and vegans combined had 44% lower odds of hypertension, an important finding given hypertension is normally so prevalent in Black communities; no benefit was seen among those who cut out all other meat but continued to eat fish. The same thing was found for total cholesterol and LDL cholesterol: the odds were cut in half among Black vegetarians and vegans. “As with non-[B]lacks, these results suggest that there are sizeable advantages to a vegetarian diet in [B]lack individuals,” the researchers conclude.
What happens when vegetarians are compared with vegans? The study’s title gives it away: “Cardiovascular Disease Risk Factors Are Lower in African-American Vegans Compared to Lacto-Ovo-Vegetarians.” This is something we’ve known about when Caucasian vegans have been compared to vegetarians. However, it was not known whether African American vegans had a more favorable cholesterol profile until this study. The results showed significantly lower LDL cholesterol in vegans. Now, of course, the vegans were also significantly slimmer, with an average weight in the normal range, compared to the overweight vegetarians. But even after taking that into account, those eating more plant-based had significantly lower cholesterol, as you can see below and at 7:11 in my video.

So, plant-based diets have tremendous potential to promote health among Black people in the United States. In fact, they may have an even greater benefit. For example, African Americans have an excess burden of chronic kidney disease, not only because they have more high blood pressure and diabetes, but also due to genetic factors. Between 8% and 12% of African Americans are carriers of the sickle cell trait, which places them at significantly higher risk of kidney disease. While Black people represent a relatively small fraction of the U.S. population, they account for more than a third of all patients on dialysis due to chronic kidney disease. And that’s where plant-based diets can come in, shown to protect against both the development and progression of chronic kidney disease.
Three-quarters of Black people are lactose-intolerant, too, so they would stand to benefit even more from eating a plant-based diet. “It is unacceptable that for decades, the American healthcare system has failed African Americans and other minority communities in both primary and secondary [cardiovascular disease] prevention,” but that just makes it all the more important for them to take the reins of their own health destiny.
Doctor’s Note
Food and tobacco aren’t the only products with marketing targeted at Black Americans. I previously covered the dangers of Johnson & Johnson’s talcum powder in Talcum Powder and Fibroids.
For more information on this topic, check out this webinar hosted by the Plantrician Project: https://plantricianproject.org/global-health-disparities-a-dialogue.


November 17, 2026
Is Bone Density Linked to Diet? It May Come Down to Body Size
Those eating a plant-based diet tend to be so much slimmer that their bone mass may suffer.
Osteoporosis affects an estimated 200 million people worldwide. Translating to “porous bone,” osteoporosis is a disease characterized by excessive bone loss, reduced bone formation, or a combination of both, which can weaken bones and increase the risk of fractures. “Bone mineral density (BMD) is the most robust and consistent predictor of osteoporotic fracture.” What can we eat to boost our bone density? Well, we know that increased consumption of plant foods is associated with increased bone mineral density.
There’s an “extensive range of micronutrients and phytochemicals packaged within plants” that can be powerful promoters of bone health, so “healthcare professionals should be encouraged to advise the increased consumption of plant based foods, particularly in mid-life, irrespective of the clients’ underlying dietary pattern”—meaning no matter how much meat or junk is eaten, adding more healthy plant foods may help prevent the development of osteoporosis. On the other hand, a more “animal-sourced nutrient pattern” has been associated with a higher risk of fractures, suggesting that a more animal-based diet is related to bone fragility. So, one would expect less osteoporosis in those eating plant-based diets, but you don’t know until you put it to the test.
The first study, “Incidence of Osteoporosis in Vegetarians and Omnivores,” was published nearly 50 years ago and found that the measured bones were significantly denser in the vegetarians than in the omnivores. In fact, the average bone densities of the vegetarians in their 70s was greater than that of the meat-eaters in their 50s. The bottom line: “These results suggest that there is less likelihood of vegetarians developing osteoporosis in old age.” It turns out, though, that the researchers screwed up. DEXA scanning, which is what we use now, didn’t come online until the 1980s. So, the researchers were using just regular x-rays and confused the readings, giving darker bones on x-rays a higher score, even though darker bones actually indicate “a lesser bone mass than a lighter image.” Their conclusion should have been reversed: The vegetarians had worse bone mineral density.
Fast forward about 40 years, by which time nine studies had been done on thousands of individuals. All in all, “[t]he results suggest that vegetarian diets, particularly vegan diets, are associated with lower [bone mineral density], but the magnitude of the association is clinically insignificant,” meaning the difference was so small as to not really matter out in the real world, reinforcing the fact that “vegetarian diets have no clinically detrimental effect on bone health.”
It’s important to note that the findings of lower bone mineral density didn’t fully control for key confounding factors, such as differences in body weight. We know that people who are obese have stronger bones. Why? Because they’re essentially weight-lifting all day, every day. Walk around with a 100-pound backpack every day, and your bones would grow stronger, too. That’s how to build strong bones: weight-bearing exercise. So, people who weigh more have denser bones. Vegetarians and especially vegans have such low rates of obesity that no wonder, on average, they would have lower bone density. The researchers didn’t take weight into account, but if the difference they found isn’t even clinically significant, who cares? “Is ‘vegetarianism’ a serious risk factor for osteoporotic fracture?” As of 2009, the answer to that question was no. “Vegetarianism is not a serious risk factor.”
By 2018, the latest meta-analysis on veganism, vegetarianism, and bone mineral density included 20 studies, involving tens of thousands of participants. It found lower bone mineral density among vegetarians and vegans compared with meat-eaters. The researchers concluded that vegetarian and vegan diets need to be “appropriately planned” to preserve their bones. But did they account for the obesity factor?
No, they did not. They just used what are called “crude risk ratios”—meaning no adjustments are made for confounding factors like weight—so they didn’t control for things like age, smoking, obesity, or exercise, making the results really “uninterpretable.” But no one had gone through the trouble of going back through all those studies and making the proper adjustments. Then, in 2020, researchers did just that. The title of their study gives away what they found: “Differences in Bone Mineral Density between Adult Vegetarians and Nonvegetarians Become Marginal when Accounting for Differences in Anthropometric [Body Size] Factors.” Yes, bone mineral density values were significantly lower among vegetarians than among nonvegetarians, which is the case with nearly every study on bone mineral density and excess body weight, as you can see below and at 4:58 in my video Do Vegans Have Lower Bone Mineral Density and Higher Risk of Osteoporosis?.
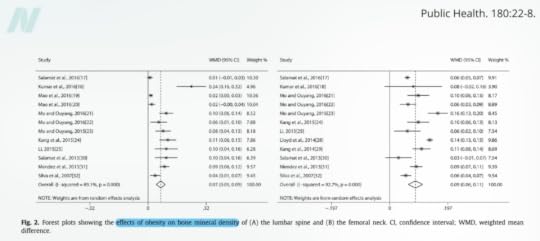
But forget clinical significance—these differences even lost statistical significance after adjusting for body size factors, suggesting that lower bone mass among vegetarians is largely explained by their lower Body Mass Index (BMI) and waist circumference. Thus, it’s not so much the composition of vegetarian and vegan diets as the fact that people who eat them tend to be much slimmer.
Now, a small yet statistically significant difference remained for total lower spine density, a difference of 0.03 g/cm2. This was dismissed as having little clinical relevance, but is that true? If the reproducibility of bone mineral density measurements in daily medical practice is considered, repeated tests performed back to back show some scatter in the measurements, as you can see at 5:44 in my video.

So, a significant difference really has to be more than the inherent variation. Indeed, expressed as the smallest detectable difference, a bone mineral density disparity of at least 0.05 g/cm2 at the spine is needed before it can be considered a significant change, so there does appear to be little clinical relevance. However, even if vegetarians and vegans basically have the same bone density at the same weight, everyone who is skinny is at risk. Low BMI is a risk factor for fractures; so, “all persons in a low body weight category consuming any kind of diet should be monitored for osteoporosis.”
Doctor’s Note
Stay tuned for more on actual bone fracture rates. In this blog, I’m just setting the stage.
In the meantime, check out some of my other videos on bone health:
Alkaline Diets, Animal Protein, and Calcium LossPhytates for the Prevention of OsteoporosisIs Milk Good for Our Bones?Are Calcium Supplements Safe?Are Calcium Supplements Effective?Almonds for OsteoporosisPrunes for OsteoporosisNovember 12, 2026
Do Meat-Eaters Have More Antibiotic Resistance in Their Guts?
Those eating plant-based have a reduced load of antibiotic resistance genes in their gut.
There are nearly one million Salmonella and Campylobacter infections in children 10 years and younger each year in the United States alone. Some of these infections are severe, causing meningitis and death, and requiring treatment with antibiotics. However, there’s an increasing problem of antibiotic resistance among these bugs that threatens our ability to treat them. Part of the issue is that the same life-saving, miracle-drug antibiotics are being squandered in animals raised for food for things like growth promotion in unhygienic, crowded conditions, which increases the likelihood that pathogens like Salmonella or Campylobacter will become resistant. (I’ve done a bunch of videos on this.) There’s another problem. The resistance determinants, the genes that encode antibiotic resistance, may be transmitted from farm animals to humans through the food supply. Most antibiotic-resistant bacteria have mobile genetic elements—these little circles of DNA called plasmids—that carry the resistance genes that they can pass on to other bacteria, including those in our own gut.
Farm animals are, therefore, “a reservoir of antibiotic resistance genes and a potential vector for transmission” of these resistance genes to the human intestinal microbiota. In one study, researchers used a model that mimics the human intestines to assess the transfer of an antibiotic-resistance plasmid from E. coli originating from a chicken raised for meat to bacteria in the human gut. And it happened within two hours. This spread of antibiotic-resistance genes presents “an alarming scenario,” “a growing concern that antibiotic resistant bacteria present on food can transfer their resistance genes to the inherent gut microbiota of the consumer,” as you can see here and at 1:51 in my video Antibiotic Resistance Genes in the Guts of Vegetarians vs. Meat-Eaters.

But you don’t know until you put it to the test. Researchers compared antibiotic-resistance gene loads in the gut bacteria of vegans, vegetarians, and omnivores. You’d think the results might be obvious, but antibiotic-resistance genes are spread by applying manure to agricultural fields of fruits and vegetables. Yes, massive antibiotic use in animal farming is thought to be the greatest contributor to antibiotic-resistant bacteria in foods of animal origin, such as meat, eggs, and dairy. However, sewage from treated animals may impact vegetables grown on fertilized fields, but it was largely unknown whether, and to what extent, antibiotic-resistant bacteria are being transferred to vegetables and then to the human gut. That is, until researchers looked for antibiotic-resistant genes against sulfa drugs like Bactrim, tetracyclines, penicillins and cephalosporins, and streptomycin-type antibiotics. They found both omnivores and vegetarians showed a significantly higher antibiotic-resistant gene load in their guts compared to vegans.
There wasn’t a significant difference between omnivores and vegetarians, but vegans had significantly lower loads than both omnivores and vegetarians—“the first evidence that a vegan life style is associated with a reduced load of human gut [antibiotic-resistant genes],” but not the last. There were fewer tetracycline-resistance genes in vegan guts and more vancomycin-resistance genes in the guts of those who eat meat. That’s no surprise, since they found a correlation between tetracycline-resistance genes and the intake of eggs, milk, and cheese, and a higher incidence of vancomycin-resistance genes was found in those who ate eggs, poultry, fish, and seafood. Vancomycin is one of our antibiotics of last resort, used to treat serious life-threatening strep and staph infections like MRSA.
Despite the links to dairy and eggs, just cutting out meat has indeed been shown to offer an advantage in some studies, as bacteria obtained from meat-eater stool samples showed resistance to a greater number of antibiotics and carried more tested antibiotic-resistance genes compared to vegan or vegetarian stool samples.
Doctor’s Note
The combined lobbying might of Big Ag and Big Pharma has prevented the United States from following the recommendations of nearly every major medical and public health entity to restrict the use of life-saving drugs to prop up agribusiness. Shame on the animal agriculture and pharmaceutical industries. More on this unacceptable practice in:
Antibiotics: Agribusinesses’ Pound of FleshPast the Age of Miracles: Facing a Post-Antibiotic AgeSuperbugs in Conventional vs. Organic ChickenFoster Farms Responds to Chicken Salmonella OutbreaksUrinary Tract Infections from Eating ChickenWhat About Kosher and Organic Chicken?The Human Health Effects of Cultivated Meat: Antibiotic ResistanceNovember 10, 2026
Are Rare Sugars Like Allulose Actually Healthy?
Are rare sugars like allulose a healthy alternative to traditional sweeteners?
Allulose is a kind of low-calorie sugar that exists naturally in very small quantities but is now industrially produced as a commercial sweetener. It’s said to have advantages that make it comparable to erythritol as a sugar substitute. It’s also said to have anti-diabetic effects, but that study was on obese mice. Allulose decreases LDL cholesterol levels in hamsters fed a high-fat diet and is said to have a substantial impact on obesity in lard-munching mice, but what about men and women?
In a petri dish, allulose inhibits fat cell precursors from maturing into fat cells and reduces the amount of fat accumulation within fat cells. Below are before-and-after pictures when regular sugar was replaced with allulose; the fat is stained red. You can also check out the photos at 0:56 in my video Is Allulose a Healthy Sweetener?.
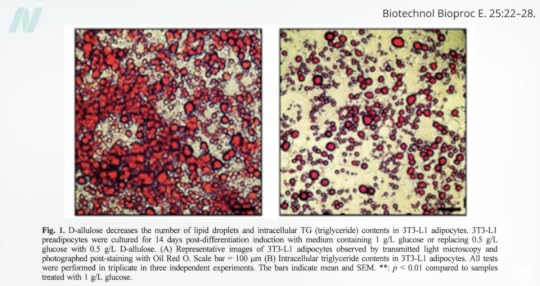
The researchers concluded that allulose might be a promising sugar substitute for an anti-obesity diet, but you don’t know until you put it to the test.
In another study, researchers gave people about a teaspoon of allulose a half hour before eating a meal. Compared to the no-sugar control group, the allulose group started burning more fat. The researchers concluded that allulose enhances after-a-meal fat burning, “indicating that it could be a novel sweetener to control and maintain healthy body weight, probably through enhanced energy metabolism.” First of all, it was only 15 calories of fat burned over that four-hour period. They didn’t burn more calories overall either. They just switched from burning carb calories to fat calories, and they may have switched back later and made up the difference over the course of the day.
We can’t just look at one meal—we need to track people’s actual weight over time. So, researchers set up a study comparing high-fructose corn syrup to the weight-reducing effect of a syrup that included about 5% allulose. The results showed significant decreases in body fat, body weight, and waist circumference with the syrup, but it was a proprietary mixture and, frankly, anything would look good against high-fructose corn syrup.
I found the study I’d been looking for: Researchers evaluated the effect of allulose for fat mass reduction in humans. More than a hundred people were randomized to a placebo control (sucralose) or a teaspoon of allulose twice a day, or one and three-quarter teaspoons twice a day. Despite no change in physical activity or calorie consumption between the two groups, body fat significantly decreased after allulose supplementation. Researchers even took CT scans so they could tell where the fat was disappearing from.
Now, the drop in body fat was only about two pounds over 12 weeks, and the drop in abdominal fat in the higher-dose group was almost totally a drop in subcutaneous fat, the flabby superficial fat, not the deeper, dangerous visceral fat that really matters for health. But still, the body fat loss despite no change in calorie intake was similar to what was seen in the mice. However, the hamster effect did not materialize—there was no significant change in LDL cholesterol in either of the allulose groups. What are the purported anti-diabetes effects?
If people chug a beverage with up to about two teaspoons of allulose alone or with a big load of rapidly digesting carbs, the allulose alone has predictably no influence on blood glucose or insulin concentration. Yet, when they consume allulose along with the refined carbs, there is actually a suppression of the elevation of blood sugar and insulin, and by a significant amount—a 30% drop in blood sugar and insulin levels over a two-hour period.
This may be because the presence of allulose impairs the absorption of sugar through the intestinal lining, because they all might be competing for the same sugar transporter. But who’s chugging maltodextrin? What about eating a regular meal? One study looked at people with borderline diabetes who could use some blood sugar spike suppression. A randomized, double-blind, placebo-controlled crossover experiment tested what drinking one and a quarter teaspoon of allulose in a cup of tea with a meal would do, and there was indeed a significant drop, though only about 15%.
The researchers also did a second experiment randomizing people to a little over a teaspoon of allulose three times a day with meals for 12 weeks. There didn’t appear to be any adverse side effects, but there also weren’t any weight loss effects in contrast with the other study. So, the body fat data are mixed, and so too are the sugar data. One study found no effects of allulose on blood sugars in healthy participants, though a similar study on people with diabetes did. A systematic review and meta-analysis of all such controlled feeding trials suggested that the acute benefit on blood sugars was of “borderline significance,” and it’s unclear whether this alone could translate into meaningful improvements in blood sugar control over time. So, maybe it’s not enough to just add allulose. You might actually have to also cut out the junk.
Although the ability to suppress blood sugar responses is the most well-studied aspect of allulose, I do want to cover just one last angle. Researchers found that allulose extends the lifespan of a tiny roundworm called C. elegans through a dietary restriction mechanism, even though the worms being studied ate the same amount of food as the control group. Two months in, just a few percent of the control group were still alive, whereas twice as many in the low-allulose group and about 25% in the higher-allulose group were still alive, as you can see below and at 5:53 in my video.
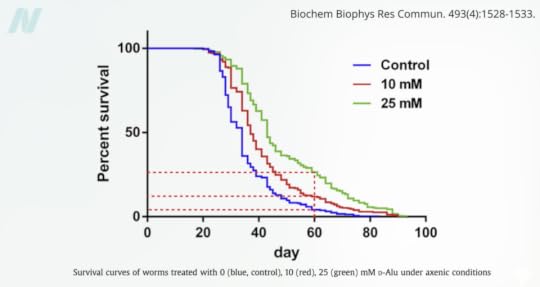
It may have worked by boosting the expression and activities of antioxidant enzymes in the body, extending lifespan by mopping up free radicals. But who cares about the survival curves of worms?
Well, C. elegans is a well-studied model of aging and longevity, mostly just for convenience’s sake, but it does share most of the longevity genes or pathways researchers are interested in. It would be nice to see experiments on human cells, at least, and here we go: A study looked at the effect of allulose on free radicals and oxidative stress in human coronary artery endothelial cells, the cells that line the inside of our arteries. Add a bunch of sugar, and free radical levels shoot up, but add the same amount of sugar along with some allulose, and it’s as if you never even added the sugar, as you can see below and at 6:41 in my video.
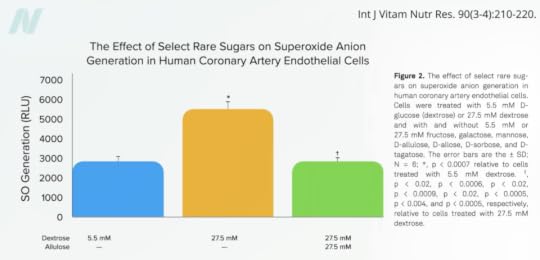
This then translates to inhibiting the expression of an inflammatory marker that plays a role in the buildup of atherosclerotic plaque. However, it’s still too early to make conclusions about the clinical relevance of these data.
So, are these rare sugars like allulose healthy alternatives to traditional sweeteners? Considering the variety of potentially beneficial effects of allulose without known disadvantages from toxicological and metabolic studies, “allulose may currently be the most promising rare sugar,” but how much is that saying? We just don’t have a lot of good data from human studies, therefore “it may be too early to recommend rare sugars for human consumption.”
Doctor’s Note
If you missed the previous blog, see Can Allulose Replace Sugar?.
The healthiest sweeteners are whole foods—fresh, frozen, or dried fruits like dates. Here is my simple (and delicious) recipe for date syrup.
November 5, 2026
Can Allulose Replace Sugar?
How safe are fourth-generation sweeteners, such as the rare sugar allulose?
First, there was sugar and high-fructose corn syrup, the original industrial sweeteners. They were cheap, but they had lots of empty calories and contributed to diseases such as obesity, type 2 diabetes, cavities, and metabolic syndrome. Then came the second-generation sweeteners, the artificial sweeteners in the colored pastel packets: NutraSweet, Splenda, and Sweet’N Low. They have practically zero calories, but there have been reports of adverse effects, prompting caution. For example, artificial sweeteners were found to induce glucose intolerance by altering the gut microbiome, thereby producing “the counterintuitive effect of inducing metabolic derangements.” (They also taste kind of funny.) Enter the third-generation sweeteners: sugar alcohols, such as sorbitol, xylitol, and erythritol. They’re low-calorie sweeteners; however, their laxative effects can create difficulties. That brings us to rare sugars like allulose, which are natural sweeteners with a sugar-like taste and low or zero calories.
For those who haven’t heard of allulose, it’s been through a bit of a rebranding—kind of like the morphing of rapeseed oil into canola oil, which forced a Canadian community to update its town slogan, as you can see below and at 1:29 in my video Does the Sweetener Allulose Have Side Effects?.

Allulose used to be called psicose, derived from the antibiotic from which it was isolated, a strange origin story for a sweetener. In the journal Frontiers in Bioengineering and Biotechnology, emphasis is placed on the fact that allulose is “a real and natural sugar rather than an artificial sweetener,” but, ironically, if you look at the reference it cites, it talks about how allulose is made via “functionalized polyhydroxyalkanoate (PHA) nano-beads decorated with D-tagatose 3-epimerase (DTE)” and “produced in recombinant endotoxin-free” branded bacteria.
Now, technically, allulose is a natural sugar—a so-called rare sugar, which the International Society of Rare Sugars defined as sugar that is “present in limited quantities in nature.” However, recent advances in technology, such as enzymatic engineering using genetically modified microorganisms, now let manufacturers produce otherwise rare sugars like allulose in substantial quantities. But small amounts have pre-existed in the food supply, so the U.S. Food and Drug Administration granted it “generally recognized as safe” status. However, that designation refers to really small amounts, like a few dozen milligrams, or a quarter of a quarter of a quarter of a teaspoon. You can see the allulose content in different foods below and at 2:51 in my video.
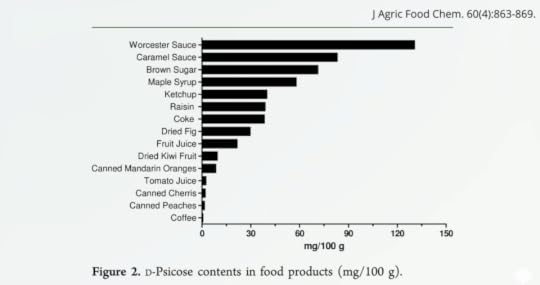
See, allulose is generated when fructose is heated. That’s why one unlucky patient kept breaking out in hives when eating foods like spaghetti, hamburgers, or cakes—he happened to be allergic to allulose, and allulose is created incidentally in the process by which high fructose corn syrup is made. So, basing the safety of allulose on the fact that it’s already been present in our food supply isn’t very convincing. You don’t know if it’s safe until you put it to the test.
Unlike table sugar, allulose is safe for the teeth—it isn’t apparently metabolized by cavity-causing bacteria to make acid and build up plaque. It doesn’t raise blood sugars, even in people with diabetes. It can be labeled as having zero calories, though technically it may have about one and a half calories per teaspoon, similar to erythritol. Also like erythritol, it is only about 70% as sweet as table sugar but has almost the same taste, texture, and performance as regular sugar. Are there any toxicities?
Allulose is considered a “relatively nontoxic” sugar. What does that mean? Well, we know a sweetener called xylitol can be extremely dangerous to dogs. As little as a half teaspoon in a 30-pound dog can be life-threatening, whereas a similar dose of allulose apparently wouldn’t be a problem, though more than half a cup at a time could make them sick. This was a single-dose study, though. The long-term safety of allulose was tested over a period of a few months and didn’t seem to cause any harmful effects at a dose of about one and a half teaspoons a day for healthy 30-pound dogs. In fact, their cholesterol actually went down, leading the investigators to suggest clinical studies to see if it’s something veterinarians should start prescribing for overweight pooches.
What happens when people consume allulose? When the dose was gradually increased to identify the maximum single dose that could be consumed occasionally, no severe gastrointestinal symptoms were noted until a dose of 0.4 g/kg of bodyweight was reached, which may be about 7 teaspoons, with severe symptoms of diarrhea occurring at around 9 teaspoons. One might wonder who could eat that much sugar at a time, anyway? A single can of Coke has 10 teaspoons, and a bottle of Mountain Dew has nearly twice that, as you can see below and at 5:19 in my video.

So, allulose is clearly not suitable as a standalone sweetener for sugary beverages.
In terms of a daily upper limit given in smaller doses throughout the day, once intake reaches around 17 teaspoons a day, depending on body weight, people start getting severe nausea, diarrhea, abdominal pain, and headaches. So, people should probably stay under single doses of about 7 teaspoons and not exceed about 15 teaspoons for the whole day. The average American may be getting 17 teaspoons of added sugars a day, so it’s certainly not something the food industry can completely switch over to.
In this way, allulose is close to xylitol in terms of maximum single dose, whereas an average-weight man in the United States could get away with 14 teaspoons of erythritol at a time, and an average-weight woman, 15 teaspoons. That’s still not enough to sweeten a bottle of Coke, but it offers a little more leeway for sweetening tea or sprinkling on a grapefruit.
Allulose is claimed to provide health benefits, though, compared to erythritol. Fourth-generation sweeteners like allulose are said to have an advantage: “additional functions,” which you can see below and at 6:28 in my video.
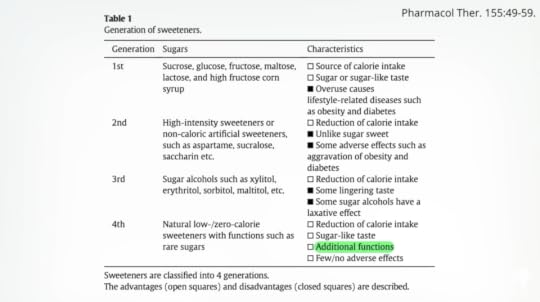
We’ll find out if that’s true in the next blog.
Doctor’s Note
Are Rare Sugars Like Allulose Actually Healthy? That’s the next blog.
I’ve covered a range of other sweeteners before in these videos:
Aspartame and the BrainErythritol May Be a Sweet AntioxidantAspartame-Induced FibromyalgiaEffect of Sucralose (Splenda) on the MicrobiomeDoes Aspartame Cause Cancer?Is Monk Fruit Sweetener Safe?November 3, 2026
A Simple Protein Swap for Healthy Aging
Swapping just 1% of plant protein in place of animal protein was associated with significantly less age-related deficit accumulation.
Based on a study of more than 400,000 people, replacing just 3% of calories of animal protein with plant protein was associated with a 10% reduction in overall mortality risk. That simple swap could translate to about an extra year of life. Egg protein—mostly found in egg whites—appeared to be the biggest offender when it came to mortality risk. Swapping 3% of calories from egg protein for plant protein was associated with more than a 20% reduction in overall mortality—greater than the reduction seen when replacing red meat with plant protein. However, it’s not just about adding years to your life, but life to your years. How do changes in dietary intake of animal versus vegetable protein affect unhealthy aging?
Healthy aging is defined as “the process of developing and maintaining the functional ability that enables wellbeing in older age.” No one wants to be vegetative, and you may be able to avoid that by eating more vegetables. A higher intake of vegetable protein was associated with less accumulation of deficits, based on functional impairments, mental health and diseases, self-reported health and vitality, and the use of health services.
Swapping in just 1% of vegetable protein calories for animal protein “led to significantly less deficit accumulation.” Don’t animal protein and animal fat travel alongside each other in the same foods? Is this just a saturated fat effect? No—even after accounting for fat, there still seemed to be something about whether the protein came from animal or plant sources, but it’s still not clear whether the beneficial health effects are due to avoiding the deleterious effects associated with animal foods or from the beneficial effects of plants, though it may be a bit of both.
A recent review in a dermatology journal on the role of a whole food, plant-based diet in preventing and reversing skin aging emphasized this point. A whole food, plant-based diet is not the same as a vegan diet. It’s possible to have a terribly unhealthy vegan diet, filled with sugar, processed oils, and white flour and no fresh fruits or vegetables. As a physician, “vegan” just tells me what a person doesn’t eat, but they actually have to, you know, eat vegetables, too. And when they do, “a whole food, plant-based (WFPB) diet can aid in the prevention, and in some cases reversal, of some of the leading chronic diseases in the United States,” as well as potentially contributing to younger-looking skin, due to telomere lengthening, maximizing our cells’ antioxidant potential, and eliminating harmful carcinogens and aging toxins, known as gerontotoxins, from entering our bloodstream.
It is no wonder “the highest life expectancy of any formally described population” in the world may be the Adventist vegetarians in Loma Linda, California, one of the world’s five original “blue zones.” The average life expectancy of Adventist vegetarian men and women is about 83 and 86 years, respectively, about 10 and 6 years longer than the general population in California. Those who eat a vegetarian diet with nuts, exercise, have a lower weight, and never smoke live about 9 to 11 years longer than people lacking these habits, as you can see below and at 3:22 in my video The Best Diet for Healthy Aging.
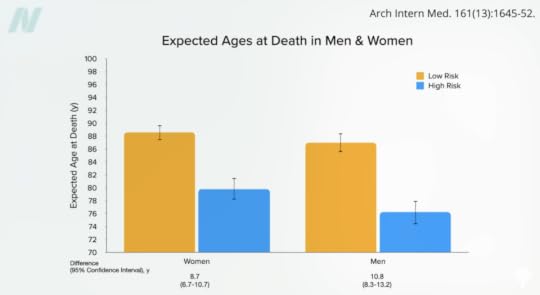
That’s like having 10 years of life up for grabs.
Now, “[s]ubstantial gains in life expectancy would only be worthwhile if they were also accompanied by a longer period of good-quality life.” Although overall well-being has not been measured directly, vegetarian Adventists have been recorded taking fewer medications and logging fewer x-ray examinations, surgical procedures, and overnight hospital stays. Their reduced prevalence of several chronic diseases alone would presumably make life more worth living.
The most feared disease associated with getting older is likely Alzheimer’s disease. Dementia is one of the fastest-growing epidemics, affecting 1 in 10 people older than 65 years of age and half of all people older than 85. Alzheimer’s is the main type of dementia, and indeed the most feared. So, when we’re talking about “plant-based diets for healthy aging,” “[p]articularly intriguing is emerging evidence that diet plays a major role in the prevention of age-related cognitive decline and Alzheimer’s disease. It has been shown that a diet rich in fruits, grains, legumes [beans], vegetables, nuts, and seeds may cut the risk of Alzheimer’s disease by more than a half.”
This evidence comes from research on the “MIND diet,” which emphasizes natural plant foods, specifically including berries (the healthiest fruits) and greens (the healthiest vegetables), while limiting the intake of animal foods and high saturated fat foods like meat and dairy.
Strictly adhering to the MIND diet was associated with a 53% reduction in risk for Alzheimer’s disease. In fact, even moderate adherence appeared to cut risk by about a third. Overall, participants with high adherence to the diet had the cognitive function equivalent to someone 7.5 years younger.
No wonder people who ate meat, including poultry and fish, “were more than twice as likely to become demented as their vegetarian counterparts”—and that rises to three times the risk when taking past meat consumption into account. This may be because “[p]lant-based diets are known to preserve body tissues from oxidative stress and inflammation, both hallmarks of chronic-degenerative diseases.” That may be why berries are so protective, since they’re so rich in antioxidants, and in terms of inflammation, those who avoid meat have a higher abundance of anti-inflammatory compounds flowing through their systems and lower levels of proinflammatory indicators like C-reactive protein. “Dietary factors also influence the effect of stress on cognitive decline. Diets characterized by high intake of animal proteins, saturated fats, and refined sugar along with low intake of plant-based foods can increase secretion of corticosteroids,” stress hormones like cortisol from the adrenal glands, which may promote the development of Alzheimer’s disease.
Then there are the gerontotoxins, like AGEs (advanced glycation end products), in our diet that may be a factor in the development of Alzheimer’s. Safe foods—foods that have low AGE content—include starches like whole grains, beans, fruits, and vegetables, whereas the main dietary sources of AGEs are broiled, grilled, fried, or roasted meats. The cooking process is important. Chicken breast has an AGE level of 1,000 KU when boiled in water (for chicken soup, for example), but that same chicken breast jumps up to 9,000 KU when broiled. Below and at 6:53 in my video is a list of the top 40 most AGE-contaminated foods tested, in terms of AGEs per serving.
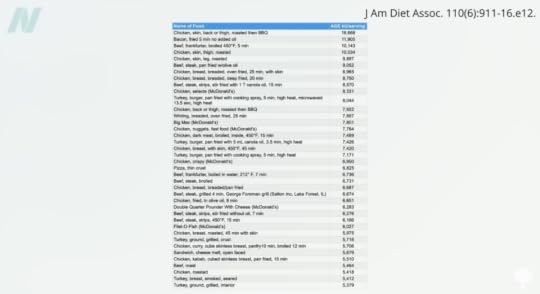
As you can see, it’s almost all meat: chicken, bacon, hot dogs, and so on. I tell people to choose raw nuts and seeds to avoid AGEs, but even roasted, toasted nuts don’t come close to making the list.
Now, of course, diet is not the only factor when it comes to reducing the risk of cognitive decline. We also need to get adequate sleep, rest, and physical activity. For example, daily brisk walks were associated with a 40% lower risk of developing Alzheimer’s later in life, and smoking may double the risk of developing dementia. But in terms of preventing Alzheimer’s with diet, the key takeaways are the following: reduce added sugars, added salt, saturated fat, animal products, and processed foods in general while eating more plants (especially greens and beans) and fruits (especially berries).
Doctor’s Note
Aging is the topic of my book How Not to Age. Check it out at your local public library.
Some of my popular videos on aging and longevity include:
How to Counter the Inflammation of AgingFruits, Veggies, and Longevity: How Many Minutes Per Mouthful?Do Flexitarians Live Longer?Methionine Restriction as a Life-Extension StrategyHow to Slow Brain Aging by Two YearsTurning the Clock Back 14 YearsLonger Life Within Walking DistanceTelomeres: Cap It All Off with DietThe Okinawa Diet: Living to 100Caloric Restriction vs. Animal-Protein RestrictionIncreased Lifespan from BeansThe Benefits of Calorie Restriction for LongevityDoes Intermittent Fasting Increase Human Life Expectancy?How to Increase Your Life Expectancy 12 to 14 YearsHow to Boost FGF21 with Diet for LongevityOctober 29, 2026
The Best Foods to Protect Against Atrial Fibrillation
What foods should we eat and avoid to reduce our risk of atrial fibrillation?
Atrial fibrillation, or Afib, is the most common clinical arrhythmia, meaning an abnormal heart rhythm, affecting millions of Americans and recognized as a global public health problem due to its “significant burden” of death and disease resulting from stroke, heart attacks, and heart failure. Is there any particular diet that may help prevent or treat it?
Recently, we learned what not to eat. Low-carbohydrate diets are associated with increased risk of developing atrial fibrillation for a variety of reasons. First, people on low-carb diets may be eating fewer anti-inflammatory foods like vegetables, fruits, and whole grains. “[R]educing intake of these anti-inflammatory foods may be one of the important mechanisms for the risk” of getting Afib. Second, a low-carb diet means increased protein and fat consumption, which may stimulate oxidative stress (the formation of free radicals), which has been shown to be associated with Afib. Finally, the effect might result from the increased risk of other cardiovascular diseases, which can set the stage for Afib. Indeed, low-carb diets are associated with an increased risk of overall mortality—dying from any cause—as well as specifically dying from cardiovascular disease and dying from cancer.
Dietary recommendations for patients with heart rhythm disorders are essentially the opposite of a low-carb diet:
Fruits, vegetables, grains, beans, and nuts every daySeafood at most a few days a weekEggs, dairy, and poultry about once a weekOther meats about once a month, in part to cut down on saturated and trans fatsYou can see the recommendations below and at 1:39 in my video The Best Diet for Treating Atrial Fibrillation.
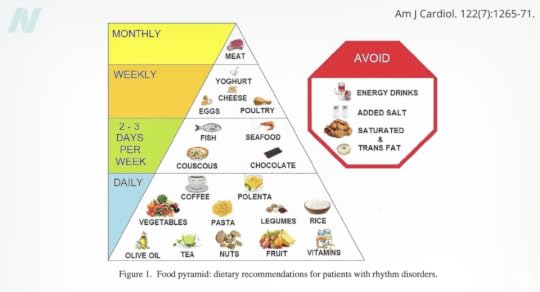
Whole food, plant‐based diets emphasizing whole grains, legumes (beans, split peas, chickpeas, and lentils), vegetables, fruits, and nuts and avoiding most (or all) animal products may play a special role, as they not only maximize protective foods, but they also exclude potentially harmful animal-based foods. For example, there’s persuasive evidence that avoiding certain foods like alcohol and dark fish may beneficially affect atrial fibrillation.
That finding about dark fish comes from the Framingham Heart Study, which classifies “dark fish” as salmon, mackerel, swordfish, bluefish, and sardines. In an exploratory analysis, researchers found that participants who consumed more than four servings of dark fish a week had about a whopping sixfold higher risk of developing Afib, though the intake of fish in general didn’t seem to have any effect.
It’s unclear exactly why alcohol is so bad when it comes to arrhythmias, but each drink per day may be associated with as much as an 8% increase in the relative risk of Afib, though drinking coffee or caffeine in general does not seem to be related to arrhythmia risk.
Where plant-based diets really shine, though, is in Afib risk factor management. “Plant‐based diets may reduce the likelihood of many traditional risk factors that are associated with [Afib], including hypertension, hyperthyroidism, obesity, and diabetes.”
High blood pressure is one of the major risk factors, accounting for about one-fifth of all new cases of Afib. This is where a plant‐based diet can come in—it can improve vasodilation (the ability of the arteries to expand naturally), provide anti‐inflammatory and antioxidant effects, increase potassium intake, and decrease blood viscosity (or sludginess).
In terms of hyperthyroidism, excluding all animal foods from one’s diet was associated with half the prevalence of hyperthyroidism compared with those who eat meat, while vegetarian and fish-only diets were associated with intermediate protection.
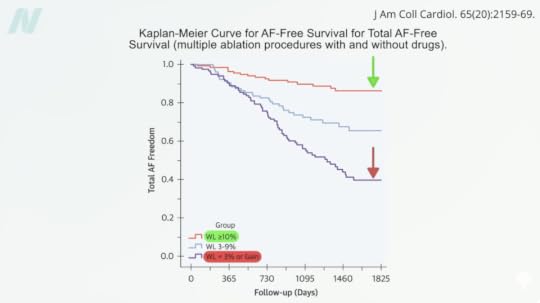
Having excess body fat may be responsible for about another fifth of all Afib cases, but the good news is that significant weight loss is associated with a sixfold greater freedom from atrial fibrillation. As you can see below and at 4:32 in my video, among overweight participants with Afib, those who lost 10% or more of their body weight had only a 10% chance of still having Afib five years later. In contrast, those who lost less than 3% of their weight—or gained weight—were 60% likely to still have Afib.
As you can see below and at 4:38 in my video, these are all the atrial fibrillation risk factors that can be prevented, arrested, or even reversed with a healthy enough plant-based diet: high blood pressure, type 2 diabetes, obesity, systemic inflammation, and heart disease.
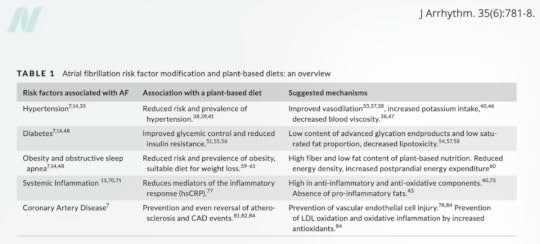
“In light of these findings, dietary modifications are of paramount importance.” But you don’t know if they could actually cure atrial fibrillation until you put it to the test.
Unfortunately, all we have are case reports, but this one is quite compelling: an 82-year-old man with polypharmacy—meaning on a bunch of different medications, due to coronary artery disease, a history of heart attacks, ischemic cardiomyopathy, high cholesterol, high blood pressure, and persistent atrial fibrillation—who presented with cognitive impairment, memory loss, fatigue, and weakness. Now, if you’re not going to change the diet and lifestyle that led to all the problems in the first place, then drugs can certainly be better than nothing. Yet, commonly used blood pressure and cholesterol-lowering medications actually provide little absolute risk reduction and pose significant risk of adverse effects, as I’ve talked about before. So, this man decided to start treating the underlying cause. He started a whole food, plant-based diet with moderate physical activity, resulting in a rapid reduction of high blood pressure and high cholesterol and the discontinuation of antihypertensive, statin, and beta-blocker drug therapy. The patient also reported a reversal of impaired cognition and symptoms linked to atrial fibrillation and ischemic cardiomyopathy, including fatigue, light-headedness, and weakness.
Check out his results below and at 6:41 in my video.
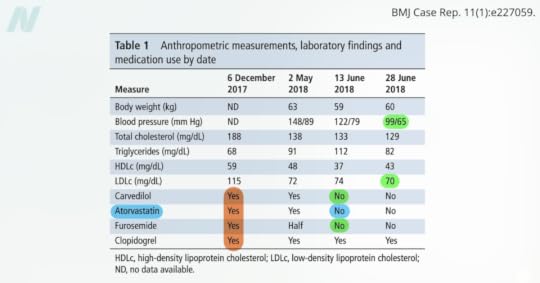
After adopting a healthier diet for about three months, his LDL cholesterol dropped by 37%, falling from 115 mg/dL to 72 mg/dL. You might point out that he was still taking cholesterol-lowering statin medication at that time, but even after his doctor discontinued the statin and blood pressure medications, his cholesterol remained low and his blood pressure completely normalized. What happened to his atrial fibrillation? Completely resolved.
Here’s how the patient described it. “In December 2017, I suffered a near-fatal heart attack and was rushed to the hospital. I immediately had a stent put in. The following day, I was prescribed a number of drugs to manage my condition. My brain fog got worse and I felt tired all the time…I decided enough was enough. I had already lost four years of my life to medication-induced brain fog. I wasn’t going to sacrifice more.” He had been eating a wholesome Mediterranean diet, but he was then educated on the benefits of cutting out meat, cheese, oil, and wine and eating more fresh vegetables. “I now have the strength to lift weights and walk and run on the treadmill an hour every day. I feel more alive than I have for years. I wake up each morning with a clear head and happy heart, grateful to not have to take a handful of drugs. Even though I’m not perfect with my diet, I’ve seen huge benefits from eating this way. My blood tests have shown remarkable improvement, which keeps me motivated to stay on track.” Because of his improvement, his cardiologist suggested he could stop taking his last remaining medication. “Eating this food gave me an opportunity to reclaim my health.”
Doctor’s Note
This important blog is a long time coming. In previous videos on Afib—Red Fish, White Fish; Dark Fish, Atrial Fibrillation and Omega 3s, Prostate Cancer, and Atrial Fibrillation—I only touched on the fish connection.
I previously reported on the dangers of low-carb diets in:
Atkins Diet: Trouble Keeping It UpPaleolithic LessonsWhole Grains May Work as Well as DrugsLow-Carb Diets and Coronary Blood FlowAlzheimer’s Disease: Grain Brain or Meathead?Does a Ketogenic Diet Help Diabetes or Make It Worse?Keto Diets: Muscle Growth and Bone DensityThe video I mentioned about the risk of medications is Why Prevention Is Worth a Ton of Cure.
October 27, 2026
Are Supplements the New Snake Oil?
There is little guarantee that a dietary supplement will actually contain what is advertised on the packaging and not have undeclared contaminants.
In one of my videos a few years ago, I talked about how press releases on the latest science coming out of even top medical centers were filled with overstatements and omissions. Medical journal press releases suffered from similar problems, and press releases from the drug companies were no different, filled with hype and exaggeration. What about press releases issued by the supplement industry? (I’m not even talking about supplement manufacturers, but trade organizations representing the multibillion-dollar dietary supplement industry.)
Researchers found that 100% of supplement industry press releases contained “spin,” meaning “strategies to hype or denigrate findings” to distort clinical studies’ results. Here’s the wild part: Industry press releases advocated for supplement use in response to more than 90% of studies reporting no benefit or harm. Let’s say a study is published showing a supplement may actually be harmful. The vast majority of independent institutions like the National Institutes of Health and mainstream media reports would likely warn people to avoid it. But most industry trade organizations would essentially say, Harm? Go for it! Buy an extra bottle. The numbers are illustrated below and at 1:24 in my video Supplementation Regulation and Side Effects: Efforts to Suppress the Truth.
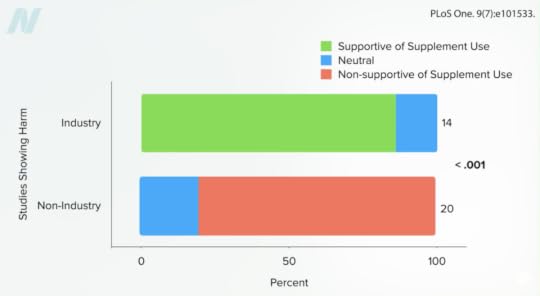
“It is therefore likely that the propagation of the ‘spin’-enriched industry press releases contributes to the ongoing, and even burgeoning, enthusiasm for use of supplements in the face of accumulating evidence of their ineffectiveness and, in some cases, harm.” Indeed, in some cases, people are paying to make themselves sick. Sadly, the science may not even matter to many supplement users. Most dietary supplement users said they would be “minimally influenced” by independent, taxpayer-funded studies that contradict the supplement manufacturers’ efficacy claims. Only about one-fourth of users said they would stop taking a supplement if public health authorities stated that it was just a waste of money.
The “snake oil salesman” wasn’t just a stereotype. He was actually a real person: Clark “the Rattlesnake King” Stanley. In 1916, it was discovered that Stanley’s snake oil, in fact, contained no snake oil at all—it was basically spicy moth repellent mixed with turpentine. Prosecuted under the newly enacted Pure Food and Drug Act, he was ultimately fined a lofty sum of $20. A century later, here we are with snake oil coming out of our ears—there’s a vast number of supplements marketed and sold without routine oversight. Now, the supplement industry bristles at such talk, saying that the industry is regulated to protect consumers. It’s true there are definitely laws on the books, but “[t]he ability of regulators to successfully carry out this mission, however, is hampered by the sheer number of products.”
The U.S. Food and Drug Administration (FDA) estimates more than 85,000 dietary supplement products are currently available in the United States alone. The sheer number of products, combined with the underreporting of adverse side effects, the difficulty of successfully prosecuting offenders, and the ease with which suppliers can rebrand products removed from shelves, has created a largely unregulated environment. “In the real world, there is little guarantee that a supplement will even contain what is advertised on the packaging and not contain unlisted ingredients, potentially leading to significant harms,” resulting in an estimated 23,000 emergency room visits every year. Now, of course, prescription drugs don’t just sicken but kill many more, making them perhaps the third leading cause of death, wiping out more than 100,000 Americans each year, but still, the less death and disability, the better.
Dietary supplements are often adulterated with undeclared pharmaceuticals—most often found in supplements for erectile dysfunction, weight loss, diabetes, and high blood pressure—which could represent “an enormous risk to consumers.” But what about supplement manufacturers that say they have independent, third party–certification of purity? There is a practice called “dry labbing,” a dirty little secret in the supplement industry, where quality assurance labs just rubber-stamp fake documents. And if you think that’s outrageous, check out the story of β-methylphenylethylamine (BMPEA).
A researcher at Harvard published a paper replicating prior research from the FDA detecting a designer amphetamine-like stimulant, BMPEA, in various supplements sold in the United States. In response, one of the offenders, Hi-Tech Pharmaceuticals, which manufactures weight-loss supplements like Black Widow and Yellow Scorpion, sued the researcher for libel, slander, and product disparagement, originally seeking $200 million in damages.
This was all documented in a piece by STAT, which is an excellent source of medical journalism that I recommend. The head of Hi-Tech “openly admitted that he was ‘hoping that we were able to silence this guy.’” Although ultimately unsuccessful in court, the lawsuit effectively sent a warning to other researchers. In fact, Hi-Tech’s CEO is reported to have said that he “hope[s] that the long and costly legal battle will scare away other academics from investigating the supplement industry.”
Doctor’s Note
The video I mentioned is Spin Doctors: How the Media Reports on Medicine.
I’ve covered the shady and unregulated nature of the supplement industry before. Check out:
Dietary Supplement Snake OilHeavy Metals in Protein Powder SupplementsSome Dietary Supplements May Be More Than a Waste of MoneyBlack Raspberry Supplements Put to the TestDangers of Dietary Supplement DeregulationSTAT is the medical journalism site I referred to. You can see it here.
October 22, 2026
The Best Foods to Fight H. Pylori
What food can eradicate H. pylori in the majority of patients?
The salting and pickling of fish produce a novel DNA-mutating chemical called CMBA, which is formed from a reaction of salt, nitrite preservatives, and methionine, an amino acid found concentrated in animal proteins. The nitrites can also interact with other protein components to form N-nitroso compounds, a powerful class of carcinogens found in cigarette smoke. This may explain why processed meats such as bacon, ham, hot dogs, lunch meat, and sausage have been tied to increased stomach cancer risk, but this extends to fresh, unprocessed, unsalted meats as well.
But isn’t most stomach cancer caused by an infection with a stomach bacteria called H. pylori? There is a synergistic interaction between H. pylori-induced inflammation gastritis and diet in the formation of stomach cancer. Check this out: Researchers in China discovered that even genetically vulnerable individuals infected with a particularly pathogenic strain of H. pylori did not appear to be at increased risk of stomach cancer, unless they ate about an ounce or more of pork per day. (An average pork chop is about six ounces.) You can see the evidence below and at 1:22 of my video How to Treat H. Pylori Naturally with Diet.
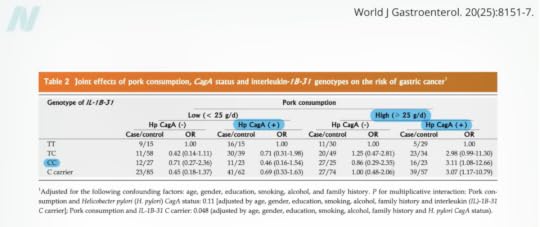
This is a striking example of how our diet can sometimes trump both our genes and environmental influences like cancer-causing infections. But is there a way to wipe out the H. pylori in the first place?
Normally, a triple antibiotic cocktail of drugs is used to kill off H. pylori, but patient compliance is difficult to maintain due to the quantity of drugs taken and the adverse side effects. Is there anything we can eat to wipe them out instead?
Decades before its detoxifying and anti-cancer abilities were discovered, sulforaphane, the remarkable compound in cruciferous vegetables, was originally described for its antimicrobial activity. After hearing anecdotal reports of individuals with H. pylori-induced peptic ulcer disease experiencing dramatic and sometimes unexpected relief after eating three-day-old broccoli sprouts, researchers at Johns Hopkins University and elsewhere decided to put broccoli sprouts to the test. Not only did broccoli sprout extracts kill antibiotic-resistant strains of H. pylori in a petri dish, but some patients who were given as little as a third of a cup of broccoli sprouts a day for a week were able to eradicate their H. pylori infection. In a randomized controlled trial comparing broccoli sprouts with alfalfa sprouts, those given the equivalent of two to three servings of broccoli a day in broccoli sprouts were able to significantly cut down on markers of both H. pylori colonization and stomach lining inflammation.
Though broccoli sprouts may be able to eradicate H. pylori in the majority of patients—56%—the standard triple-drug antibiotic therapy is much more effective with about 90% eradication. Still, for those who don’t meet the criteria for drug treatment, cruciferous vegetables may present a safe, natural way to combat H. pylori and the development of stomach cancer. A compilation of 22 population studies found that eating more cruciferous vegetables was associated with a significantly lower stomach cancer risk. Broccoli has never been directly put to the test, but garlic has.
Observational studies dating back to the 1960s on Japanese migrants have suggested that allium family vegetables—such as garlic and onions—may be protective against stomach cancer, as you can see below and at 3:43 in my video.

To date, there have been dozens of such studies published, and overall, eating lots of allium vegetables was indeed associated with significantly lower stomach cancer risk. There is evidence of publication bias, though, meaning there appears to have been other studies that failed to show such an effect, but they were shelved and never published. Even if this weren’t the case, observational studies never prove cause and effect.
For example, maybe low garlic and onion consumption didn’t contribute to stomach cancer, but rather stomach cancer contributed to low garlic and onion consumption. Decades of H. pylori stomach inflammation leading up to the cancer may have led to people choosing bland diets to avoid discomfort. You can’t know if garlic really helps until you put it to the test.
Louis Pasteur was evidently the first to describe the antibacterial effect of garlic and onion juices.
Petri dish studies have shown that garlic is effective in suppressing the growth of H. pylori at concentrations achievable in the stomach with a single clove. Even some antibiotic-resistant strains appear to be susceptible. But does this translate into stopping the growth of cancer? A randomized, double-blind, controlled trial was launched to find out.
Thousands of people at high risk for stomach cancer from 13 villages in China were randomized into various combinations of antibiotics, garlic supplements, and antioxidant supplements. Just a few weeks of antibiotics led to a significant decrease in subsequent precancerous stomach growths 7 years later and a significant decrease in subsequent stomach cancer by 15 years. What about the garlic? No benefit by 7 years and only a non-statistically significant reduction after 15 years. But in 2019, we got the 22-year update, 15 years after the study ended, and those who had taken the garlic did indeed have a significantly lower risk of subsequently dying from cancer, though interestingly the protective effect of garlic only seemed to manifest among nondrinkers.
Doctor’s Note
If you missed the previous blog, see Pickled Paradox: Kimchi’s Link to Stomach Cancer.
For more on cruciferous and allium family vegetables and cancer, see:
DNA Protection from BroccoliCancer, Interrupted: Garlic and FlavonoidsLung Cancer Metastases and BroccoliBenefits of Garlic for Fighting Cancer and the Common ColdOctober 20, 2026
Yoga Put to the Test: What the Science Really Shows
The origins of yoga go back thousands of years, and the practice of yoga for health has become popular worldwide. A 2016 survey estimated that 36 million Americans may be involved in yoga to varying degrees, for example. With so many practitioners, what do we really know about yoga?
What Are the Benefits of Yoga?
As I discuss in my video How to Prove Whether Yoga Has Special Benefits, researchers have found that yoga users have better health status and are less likely to be obese, but that could be reverse causation––meaning instead of yoga leading to better health and a normal weight, maybe being in better health, not being obese, is leading to more yoga. Same with the flipside. When you read that yoga practitioners are more likely to have mental health conditions, such as depression or anxiety, and musculoskeletal conditions, like arthritis, gout, lupus, fibromyalgia, joint pain, sprains, and asthma, yoga may be contributing to some of these conditions, like muscle sprains, but for most of them, it’s probably reverse causation—people with diseases seeking help. Are they getting it? The only way to know for sure, is to put it to the test, which we’ll explore, next.
Yoga for Mental Health
Sadly, for depression, yoga doesn’t even seem to have a benefit, compared to doing nothing. Yoga does appear to be helpful with anxiety, but not for people anxious to the extent that they’re actually diagnosed with an anxiety disorder. And, all the benefit from yoga on anxiety appears to be from the physical activity, since there appears to be no benefit compared to other types of exercise. So, unfortunately, yoga does not appear to be effective for mood and anxiety disorders.
That held up even among older adults, too. Psychologically, yoga appeared to beat out other exercises for alleviating depression in older adults, but not anxiety or perceived mental health in general.
What Does Yoga Do for Our Body?
There are some conditions for which yoga really does appear to pull ahead, though. For example, chronic nonspecific neck pain, which I cover in my video Yoga Put to the Test for MS, Back Pain, Neck Pain, Insomnia, and Breast Cancer. Based on 10 randomized controlled trials, not only was yoga better for neck pain than control groups in general––which included doing nothing, yoga also seemed to beat out active controls, other types of exercises. The authors tentatively conclude that yoga can relieve neck pain intensity, improve pain-related disability, increase range of motion, improve quality of life, and boost mood among neck pain sufferers.
What about the benefits of yoga practice compared to physical exercise in the management of type 2 diabetes? As I discuss in my video Yoga Put to the Test for Headaches, Diabetes, Osteoarthritis, and Older Adults, a significant reduction in both short-term and longer-term blood sugar control was noted in the yoga groups compared to other exercise control groups. However, the findings may need to be interpreted with caution, since nearly half of the studies didn’t define and adhere to a well-planned exercise regimen in the control group. Furthermore, an exercise intervention comparable in intensity to yoga was followed only in three out of the eight studies included. And, for what it’s worth, the majority of the studies, six out of eight, were from India.
Yoga was examined as a therapy for irritable bowel syndrome, too, and evidence from randomized controlled trials found that yoga beat out drugs and was equally effective as moderate intensity walking.
Yoga for Strength
What about compared to other exercises? Yoga pulled ahead for lower limb strength and lower body flexibility, but for improving balance, mobility, and walking speed, yoga appeared comparable.
What happened when researchers studied yoga and bone strength? They devised a 12-minute DVD of 12 yoga poses that they believed would stimulate increased bone density in the spine and both parts of the hip. It appeared yoga did provide benefit in the spine, but not the hip. In the end, though, out of the 741 patients recruited at the start of the study, only a few dozen actually sent in their bone scans as instructed. So, that’s only about 5% of the study participants. You can imagine how those who got positive results were more likely to send them in, while those who failed just kind of slunk away. So, I don’t consider this convincing evidence.
Yoga for Women
Several conditions disproportionately affect women, like insomnia. Does yoga help? Yoga works compared to nothing, but not for physically active controls. And, for cancer patients—mostly breast cancer patients—walking was found to be more effective than yoga at improving sleep. For markers of systemic inflammation in breast cancer survivors, six months of yoga had the similar effect as six months of non-yoga exercise. Same with cancer-related fatigue, and quality of life for women with breast cancer: better than nothing, but no better than other types of physical activity. Finally, for breast cancer survivors, the effectiveness of yoga interventions in breast cancer-related lymphedema, an abnormal accumulation of fluid for which there is no effective treatment, and adding yoga does not seem to help.
Yoga and urinary incontinence have been investigated, too, which I look at in my video Yoga Put to the Test for Depression, Anxiety, and Urinary Incontinence. There are two different types of urinary incontinence: urgency incontinence, defined as an involuntary loss of urine associated with a sudden strong desire to urinate, or stress incontinence, where an activity such as sneezing triggers an involuntary leak. Three months of yoga didn’t seem to significantly help overall incontinence, but it did seem to help with stress incontinence, decreasing by an average of 61% in the yoga group versus only 35% in controls with no significant changes in urgency incontinence.
See my video Yoga Put to the Test for IBS, Inflammatory Bowel, Menopause, and Osteoporosis for more information.
The Adverse Effects of Yoga
In my video The Side Effects of Yoga I discuss a systematic review included nine observational studies with more than 9,000 yoga practitioners and 9,000 non-yoga practitioners from the United States, Europe, Asia, and Australia. A considerable proportion of yoga practitioners experienced injuries or other adverse events. However, most were mild and transient, and risks were comparable to those of non-yoga practitioners. The risk of yoga-associated injuries was estimated as 1.45 per thousand hours of yoga practice––much lower than in higher-impact sports activities, such as soccer. Compared to 1.5 for yoga, runners have about 2.5 injuries per thousand hours; soccer 3.7; 5 for tennis, and an hour of yoga is more than five times safer than skiing.
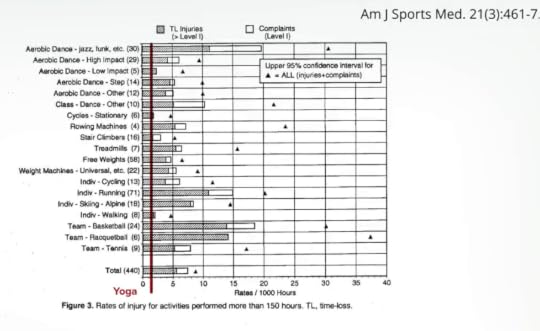
The bottom line is that like any other type of physical activity, yoga carries a risk of injury. Exercise is indeed medicine, but like any medicine, it must be prescribed appropriately. Many patients rely on their yoga practice for stress reduction. So, it is important to be mindful that being injured is the last thing you need. The higher-risk yoga poses appear to include headstand, shoulder stand, lotus and half-lotus, forward bend, backward bend, and handstand, so beginners should be beware, with particular attention paid to the spine, as this is where the highest number of injuries occur.

As with any other physical or mental practice, yoga should be practiced carefully under the guidance of a qualified instructor. Beginners should avoid extreme practices such as headstand, lotus position, and forceful breathing. Individuals with medical preconditions should work with their physician and yoga teacher to appropriately adapt postures. For example, patients with glaucoma should avoid upside-down positions, and patients with compromised bones should avoid forceful yoga practices, and practices like voluntary vomiting should perhaps be avoided completely.

